Anal and Rectal Pain: Causes, Relief and When to Seek Care
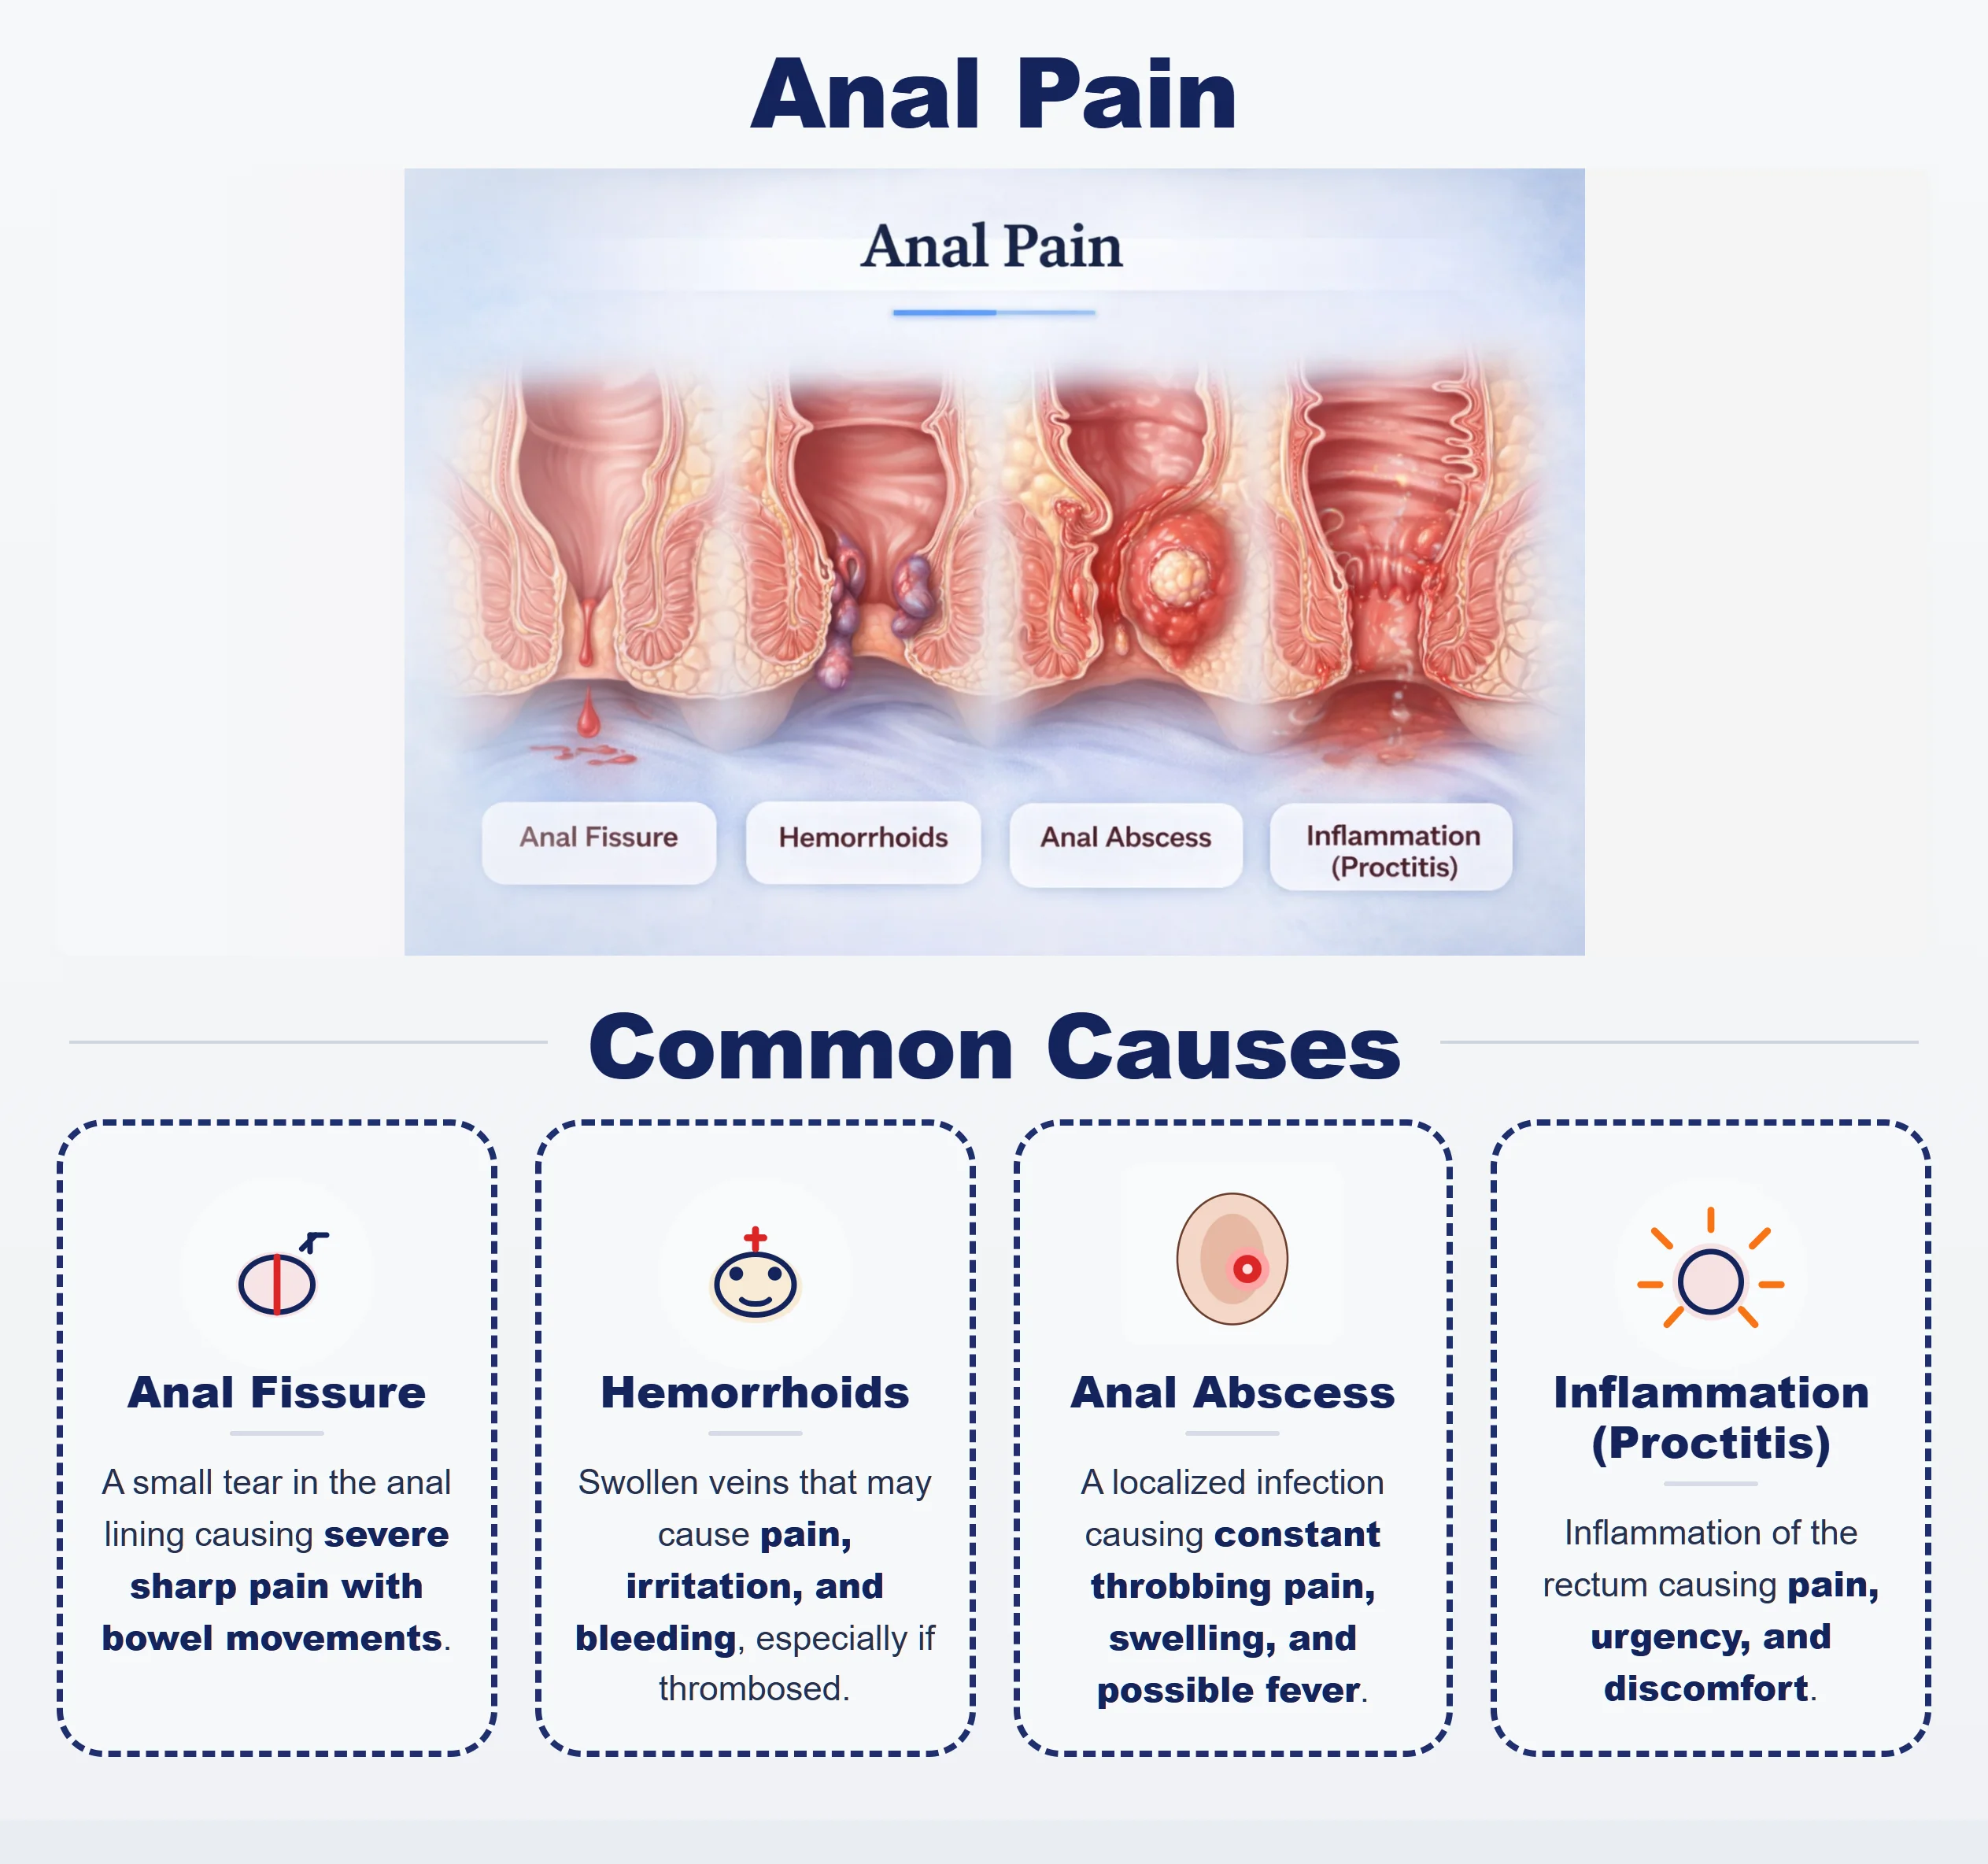
Symptoms of anal pain may include sharp pain during defecation swelling tenderness irritation or associated bleeding depending on the cause.
Anal pain or rectal pain may feel sharp, burning, tearing, throbbing, aching, or pressure-like. Common causes include an anal fissure, a thrombosed external hemorrhoid, an anal abscess, skin irritation, rectal inflammation, constipation-related injury, or pelvic-floor muscle spasm.
The timing and pattern of pain offer useful clues. Sharp pain during or after a bowel movement often occurs with a fissure. A sudden tender lump may be a thrombosed hemorrhoid. Constant or worsening pain with swelling, fever, chills, or drainage may indicate an abscess and needs prompt medical evaluation.
Seek urgent medical care for rapidly worsening pain, fever or chills, significant swelling, pus or foul-smelling drainage, heavy bleeding, faintness, or inability to pass stool or gas with abdominal swelling or vomiting.
Written and medically reviewed by Aisha Akhtar, MD, FCPS, FACS, a board-certified colon and rectal surgeon and general surgeon. Last medically reviewed: August 4, 2026
This page provides general education and cannot diagnose the cause of pain. Persistent, severe, recurrent, or worsening symptoms should be examined.
Need a private evaluation in Phoenix? Patients in Phoenix, Scottsdale, Glendale, and nearby Arizona communities may request an appointment for anal or rectal pain or call 602-932-5660.
What Can Anal Pain Feel Like?
People describe anal or rectal pain in different ways:
Sharp, cutting, or tearing pain during a bowel movement
Burning pain that continues after passing stool
A dull ache or pressure inside the rectum
Throbbing pain with swelling
A sudden painful lump near the anus
Brief attacks of severe stabbing pain
Pain that becomes worse while sitting
Soreness, itching, raw skin, or surface irritation
Pain with bleeding, mucus, pus, drainage, diarrhea, or bowel urgency
Symptoms overlap, so pain alone cannot reliably distinguish hemorrhoids, fissures, abscesses, inflammatory conditions, pelvic-floor disorders, or tumors.
Anal Pain Patterns and Possible Causes
Pain pattern
Possible causes
What to do
Sharp or tearing pain during or after a bowel movement
Anal fissure, hard stool, local injury
Arrange an evaluation if the pain is severe, persists, or occurs with bleeding
Sudden tender lump near the anus
Thrombosed external hemorrhoid, abscess
Seek a prompt examination, especially for severe pain or increasing swelling
Constant throbbing pain with fever, warmth, or drainage
Anal or perirectal abscess
Seek urgent medical evaluation
Dull rectal ache or pressure, often worse while sitting
Pelvic-floor spasm, levator ani syndrome, constipation, proctitis, deep abscess
Schedule an evaluation if persistent or recurrent
Brief stabbing pain that completely resolves
Proctalgia fugax
Discuss recurrent or changing episodes with a clinician
Persistent pain with a firm or growing lump, weight loss, or bowel-habit change
Benign anorectal disease or, less commonly, a tumor
Do not delay examination
This table is a guide, not a diagnosis.
What Treatment Is Appropriate for Anal or Rectal Pain?
Treatment depends on the cause. A fissure, thrombosed external hemorrhoid, abscess, skin condition, rectal inflammation, and pelvic-floor disorder can produce overlapping symptoms but require different care. Relief may involve stool regulation, gentle skin care, prescription medication, pelvic-floor therapy, an office procedure, or surgery, depending on the diagnosis.
Repeatedly using hemorrhoid creams without an examination can delay the correct treatment. See how anal and rectal pain are treated and arrange an evaluation when pain is severe, persistent, recurrent, or associated with bleeding, swelling, fever, or drainage.
Why Does My Anus Hurt?
The anus contains sensitive skin, muscles, glands, blood vessels, and nerves. Pain can begin when tissue tears, swells, becomes inflamed or infected, or when the pelvic-floor muscles tighten. Constipation, hard stool, diarrhea, prolonged toilet sitting, local trauma, skin products, and some infections can trigger or worsen symptoms.
The most useful diagnostic clues include:
Whether the pain started suddenly or gradually
Whether it occurs during, after, or independently of bowel movements
Whether the pain is at the opening or feels deeper inside the rectum
Whether there is a lump, swelling, bleeding, itching, mucus, pus, or drainage
Whether sitting, constipation, diarrhea, intercourse, menstruation, or pregnancy affects it
Whether fever, chills, weakness, weight loss, or a bowel-habit change is present
Many people assume every painful anal symptom is a hemorrhoid. Fissures, abscesses, skin conditions, infections, and pelvic-floor disorders are commonly mistaken for hemorrhoids and require different treatments.
Common Causes of Anal or Rectal Pain
Anal Fissure
An anal fissure is a small tear in the anal-canal lining. It commonly causes sharp, cutting, or tearing pain as stool passes, followed by burning or spasm that may continue for minutes or hours. Bright-red blood may appear on toilet paper or the outside of the stool.
Fissures may develop after hard stool, constipation, diarrhea, childbirth, or local trauma. Treatment often begins with stool regulation, warm sitz baths, and prescription topical medication when appropriate. A chronic fissure may require botulinum toxin injection or surgery after individualized discussion.
Thrombosed External Hemorrhoid
A thrombosed external hemorrhoid occurs when a blood clot develops beneath the sensitive skin outside the anus. It may appear suddenly as a firm, tender, bluish or purple lump and can cause intense pain with sitting, walking, wiping, or bowel movements.
Some improve with conservative care. Selected patients with severe symptoms may benefit from an office procedure, particularly when examined early. Fever, pus, spreading redness, or rapidly increasing swelling raises concern for an abscess rather than an uncomplicated hemorrhoid.
Hemorrhoids
External hemorrhoids can cause swelling, tenderness, itching, and pain. Uncomplicated internal hemorrhoids more often cause painless bleeding or prolapse because they are covered by less pain-sensitive tissue. Severe pain should not automatically be attributed to internal hemorrhoids; it may indicate thrombosis, prolapse with strangulation, a fissure, an abscess, or another condition.
Anal Abscess or Fistula
An anal abscess is an infected cavity near the anus or rectum. Pain is often constant and may worsen with sitting or bowel movements. Swelling, warmth, redness, fever, chills, pressure, or pus drainage may occur. A deep abscess can cause rectal pressure without an obvious external lump.
An abscess generally requires drainage. An anal fistula is an abnormal tunnel that can remain after an abscess and may cause recurrent swelling, pain, a persistent skin opening, or intermittent drainage.
Proctitis or Rectal Inflammation
Proctitis may cause rectal pain, urgency, the repeated sensation of needing to pass stool, bleeding, mucus, pus, diarrhea, or painful bowel movements. Causes include inflammatory bowel disease, certain infections, radiation therapy, and diversion after ostomy surgery. Pain with discharge, sores, bleeding, or a recent sexual-exposure concern may require testing for infectious proctitis.
Pelvic-Floor Spasm and Levator Ani Syndrome
Pelvic-floor muscle spasm can cause a deep dull ache, pressure, fullness, or the sensation of sitting on a ball. Levator ani syndrome often becomes more noticeable during prolonged sitting and may last for hours. Treatment may include pelvic-floor physical therapy, biofeedback, bowel-habit optimization, and selected medication after structural causes are excluded.
Proctalgia Fugax
Proctalgia fugax causes brief, sudden attacks of severe rectal pain that resolve completely. Persistent pain, a new lump, bleeding, fever, or drainage is not typical and should be evaluated for another cause.
Skin Irritation or Dermatitis
Diarrhea, moisture, stool leakage, excessive wiping, fragranced wipes, soap, topical products, yeast, eczema, psoriasis, and other skin conditions can cause burning, itching, soreness, or superficial pain. Treatment depends on identifying the irritant or skin condition.
Constipation or Fecal Impaction
Hard stool can stretch or injure the anal canal, cause a fissure, irritate hemorrhoids, and create rectal pressure. Severe constipation or impacted stool may cause pain, fullness, difficulty passing stool, or leakage around retained stool.
Other Possible Causes
Other causes include inflammatory bowel disease, rectal prolapse, pudendal nerve irritation, coccyx or pelvic pain referred toward the rectum, local trauma, and—less commonly—an anal or rectal tumor. Persistent pain with a firm or growing lump, recurrent bleeding, ulceration, unexplained weight loss, thinner stools, or a bowel-habit change requires examination.
What Causes Sudden Sharp Pain in the Anus?
Sudden sharp anal or rectal pain can have several causes. The timing of the pain and any associated symptoms help guide the evaluation:
Pain during or after a bowel movement: An anal fissure or local injury is possible, especially after constipation or hard stool.
A sudden painful lump: A thrombosed external hemorrhoid is possible, although an abscess can also cause a tender swelling.
Constant or worsening pain: An abscess or another inflammatory condition should be considered, particularly with fever, warmth, redness, or drainage.
Brief stabbing pain that resolves completely: Proctalgia fugax or pelvic-floor muscle spasm may be possible after structural causes are excluded.
Pain with rectal pressure, bleeding, mucus, diarrhea, or urgency: Rectal inflammation, infection, inflammatory bowel disease, or another colorectal condition may require evaluation.
A first episode of severe pain should not be self-diagnosed. Seek prompt medical assessment when the pain persists, repeatedly returns, interferes with sitting or passing stool, or occurs with a lump, bleeding, fever, swelling, or drainage.
Why Does My Rectum Hurt During or After a Bowel Movement?
An anal fissure is a common cause of sharp pain during a bowel movement or pain after pooping, particularly when the sensation feels like cutting, tearing, or passing glass. The pain may continue afterward, and a small amount of bright-red blood may be visible.
Other possibilities include:
Hard stool or constipation
Diarrhea-related irritation
A thrombosed external hemorrhoid
Inflamed or prolapsing hemorrhoidal tissue
Proctitis or inflammatory bowel disease
An anal abscess
Pelvic-floor muscles that do not relax appropriately
Trauma to the anal canal
Repeated straining and prolonged toilet sitting can worsen several of these conditions.
Pain that is severe, keeps returning, or occurs with fever, a tender lump, increasing swelling, pus, significant bleeding, or difficulty passing stool should be examined rather than managed as routine hemorrhoid discomfort.
Why Does My Anus Burn After Pooping?
Burning after a bowel movement may come from a fissure, frequent diarrhea, irritated hemorrhoids, excessive wiping, fragranced wipes, soap, moisture, stool leakage, or dermatitis. Persistent burning should not automatically be treated with hemorrhoid cream because the correct treatment depends on the cause.
Why Do I Have Rectal Pain Without Bleeding?
Pain can occur without visible blood. Possible causes include pelvic-floor spasm, levator ani syndrome, proctalgia fugax, an early or deep abscess, constipation, skin irritation, nerve pain, rectal inflammation, a nonbleeding thrombosed hemorrhoid, or internal pressure from prolapse.
The absence of bleeding does not rule out a significant condition. Deep, persistent, worsening, or recurrent pain deserves evaluation, especially with swelling, drainage, fever, urgency, or changing bowel habits.
Why Is Anal or Rectal Pain Worse When Sitting?
Sitting can increase pressure on a thrombosed hemorrhoid, abscess, irritated skin, pelvic-floor muscles, coccyx, or pudendal nerve. A visible painful lump suggests an external anorectal condition. Deep aching without a visible lump may require assessment of the rectum, pelvic-floor muscles, coccyx, and pelvic nerves.
What Causes Sudden Rectal Pain at Night?
Brief attacks of stabbing rectal pain that begin suddenly and fully resolve may represent proctalgia fugax. A first episode should not be self-diagnosed. Persistent pain or pain accompanied by a lump, bleeding, fever, swelling, or drainage requires examination for a fissure, thrombosed hemorrhoid, abscess, inflammation, or another structural cause.
Anal Pain After Intercourse or Penetration
Pain may result from friction, inadequate lubrication, a small fissure, tissue trauma, hemorrhoidal irritation, pelvic-floor spasm, or infection. Stop the activity causing pain. Seek evaluation for persistent pain, significant bleeding, fever, discharge, sores, ulcers, bowel urgency, or a recent exposure concern.
Avoid using numbing products to continue penetration through severe pain because reduced sensation may allow further injury.
Sharp Anal Pain and Lower Abdominal Pain in Women
Sharp pain in the anus together with lower-abdominal or pelvic pain in a woman should not be attributed to a single condition without an evaluation. Symptoms may arise from the anus or rectum, the bowel, pelvic-floor muscles, or a gynecologic or urinary condition, and more than one problem can occur at the same time.
Useful details include whether the pain is related to bowel movements, constipation, diarrhea, menstruation, pregnancy, urination, or intercourse, and whether there is rectal or vaginal bleeding, a painful lump, swelling, mucus, pus, or drainage. Recurrent pain linked to menstruation may warrant evaluation for pelvic-floor dysfunction, gastrointestinal disease, or, less commonly, rectal endometriosis.
Seek prompt medical care for severe or worsening pain, fever or chills, persistent vomiting, faintness, significant rectal or vaginal bleeding, marked abdominal swelling, inability to pass stool or gas, or severe symptoms during pregnancy.
Anal Pain During a Period or Pregnancy
Rectal discomfort may become more noticeable during menstruation because pelvic pain and muscle contractions can be felt near the rectum. Recurrent pain with menstruation, painful bowel movements, or cyclical rectal bleeding may require evaluation for pelvic-floor dysfunction, gastrointestinal disease, or, less commonly, rectal endometriosis.
During pregnancy, constipation, hemorrhoids, pelvic pressure, and bowel-habit changes can contribute to anal pain. New severe pain, a tender lump, fever, drainage, or significant bleeding should be discussed promptly with an obstetric clinician or colorectal specialist.
When Should You See a Doctor for Anal Pain?
Arrange an evaluation when anal or rectal pain:
Lasts more than a few days or keeps returning
Is severe or progressively worsening
Does not improve with appropriate self-care
Occurs with rectal bleeding
Is associated with a lump, swelling, skin opening, or drainage
Makes sitting, walking, sleeping, or passing stool difficult
Occurs with constipation, diarrhea, urgency, or another bowel-habit change
Develops after a previous abscess or fistula
Occurs during pregnancy or in someone with diabetes, inflammatory bowel disease, or immune suppression
Is accompanied by unexplained weight loss or a persistent change in stool caliber
A focused anorectal examination can distinguish fissures, hemorrhoids, abscesses, fistulas, infections, inflammatory disease, pelvic-floor spasm, prolapse, and less common tumors.
When Is Anal Pain an Emergency?
Seek urgent medical attention for:
Pain that rapidly worsens or spreads
Fever or chills with anal or rectal pain
Significant swelling, redness, or warmth near the anus
Pus or foul-smelling drainage
Severe constant or throbbing pain
Heavy bleeding or bleeding that does not stop
Bleeding with dizziness, faintness, weakness, or shortness of breath
Inability to pass stool or gas with marked abdominal swelling or vomiting
Severe symptoms after recent colorectal surgery or in someone with diabetes or immune suppression
These findings may indicate an abscess, spreading infection, significant bleeding, obstruction, or another urgent condition.
What Can Help Mild Anal Pain at Home?
For mild symptoms without fever, significant swelling, heavy bleeding, pus, or rapidly worsening pain, temporary comfort measures may include:
Keep stool soft and formed with dietary fiber and adequate fluids when medically appropriate
Address constipation or diarrhea with guidance from a healthcare professional
Use nonprescription pain medication only when safe for your medical history and other medicines
Do not puncture or attempt to drain a painful lump. Avoid repeatedly applying steroid, anesthetic, antibiotic, or hemorrhoid creams without a diagnosis; these products may irritate the skin, mask progression, or delay the correct treatment.
Home care does not replace evaluation for persistent, severe, recurrent, or complicated symptoms.
How Is Anal or Rectal Pain Diagnosed?
Evaluation begins with the pain’s location, timing, duration, severity, and relationship to bowel movements. The clinician may ask about constipation, diarrhea, bleeding, drainage, childbirth, pelvic symptoms, previous abscesses or surgery, inflammatory bowel disease, sexual exposure history, medications, and immune status.
Depending on the presentation, evaluation may include:
Inspection of the skin and anal opening
A gentle digital rectal examination when appropriate
Anoscopy or proctoscopy to examine the anal canal and lower rectum
Pelvic-floor muscle assessment
Testing for infection when indicated
Biopsy of a persistent or suspicious lesion
Ultrasound, CT, or pelvic MRI when a deep abscess or complex fistula is suspected
Colonoscopy or other bowel evaluation when bleeding, inflammation, bowel-habit change, age, or risk factors warrant it
The examination is adapted to the patient’s comfort and clinical condition. When pain is severe, the initial examination may be limited while an acute infection or another urgent problem is addressed.
How Is Anal or Rectal Pain Treated?
Treatment should address the diagnosis rather than simply suppressing pain.
Cause
Possible treatment approach
Anal fissure
Stool regulation, warm baths, prescription topical medication, botulinum toxin, or surgery for selected chronic fissures
Thrombosed external hemorrhoid
Conservative care or an office procedure for selected patients with severe recent symptoms
Internal hemorrhoids
Bowel regulation, office procedures such as rubber-band ligation, or surgery for selected advanced disease
Anal abscess
Drainage; additional treatment depends on infection severity and individual risk factors
Anal fistula
A procedure selected according to the tract and its relationship to the sphincter muscles
Proctitis or infection
Treatment directed at the identified inflammatory or infectious cause
Removal of irritants, gentle skin care, moisture control, and treatment of an identified skin condition
Rubber-band ligation treats selected internal hemorrhoids; it does not treat an anal fissure, external hemorrhoid, abscess, or pelvic-floor pain. Likewise, hemorrhoid creams will not correct an abscess, fistula, infection, or muscle disorder. An accurate diagnosis prevents repeated use of the wrong treatment.
Why See a Colon and Rectal Surgeon?
A colon and rectal surgeon has focused training in disorders of the colon, rectum, anus, and pelvic floor. This matters because several conditions produce similar symptoms but need very different care:
Sharp pain with bowel movements may indicate a fissure
A sudden painful lump may be a thrombosed hemorrhoid
Constant worsening pain with fever may indicate an abscess
Recurrent drainage may indicate a fistula
Deep aching pressure may reflect pelvic-floor spasm
Pain with urgency, mucus, or diarrhea may indicate proctitis
Persistent pain with a lump or bowel-habit change may require biopsy or broader colorectal evaluation
Patients do not need to determine the diagnosis before requesting an appointment.
Common causes include an anal fissure, external or thrombosed hemorrhoid, constipation, diarrhea-related irritation, an abscess, fistula, skin inflammation, proctitis, infection, or pelvic-floor muscle spasm. The pain pattern and associated symptoms help narrow the cause, but persistent pain often requires examination.
What causes sharp pain in the anus?
Sharp anal pain may result from a fissure, thrombosed external hemorrhoid, abscess, local injury, ulcer, or muscle spasm. Pain that begins during a bowel movement and continues afterward is particularly suggestive of a fissure.
What can cause sharp anal pain and lower abdominal pain in a woman?
The pain may arise from an anorectal condition, constipation or another bowel problem, pelvic-floor dysfunction, or a gynecologic or urinary condition. The relationship to bowel movements, menstruation, pregnancy, urination, and intercourse can provide useful clues, but severe, persistent, or recurrent combined pain should be medically evaluated.
How can I tell a fissure from a hemorrhoid?
A fissure usually causes sharp tearing pain during and after bowel movements, sometimes with bright-red bleeding. External hemorrhoids more often cause swelling, itching, tenderness, or a lump. Internal hemorrhoids commonly cause painless bleeding or prolapse. Because symptoms overlap, examination is the most reliable distinction.
Can hemorrhoids cause severe anal pain?
A thrombosed external hemorrhoid can cause sudden severe pain. Uncomplicated internal hemorrhoids are usually not intensely painful. Severe pain may indicate thrombosis, prolapse with strangulation, a fissure, an abscess, or another diagnosis.
Can an anal abscess look like a hemorrhoid?
Yes. Both can cause a painful lump. An abscess is more likely to cause constant worsening pain, warmth, redness, fever, chills, or pus. Because an abscess usually requires drainage, prompt assessment is important.
Can anal pain occur without bleeding?
Yes. Pelvic-floor spasm, levator ani syndrome, proctalgia fugax, an early or deep abscess, constipation, nerve pain, skin irritation, and a thrombosed hemorrhoid may cause pain without visible bleeding.
Is anal pain a sign of cancer?
Most anal pain is caused by noncancerous conditions. Persistent pain with a firm or growing lump, recurrent bleeding, ulceration, unexplained weight loss, thinner stools, or a bowel-habit change should nevertheless be examined because anal and rectal cancers can resemble benign anorectal disease.
When should I see a proctologist or colorectal surgeon?
See a colorectal specialist when pain is severe, recurrent, persistent, associated with bleeding, swelling or drainage, or not improving with appropriate self-care. A specialist can assess the anal canal, rectum, hemorrhoids, fissures, abscesses, fistulas, prolapse, and pelvic floor.
Anal and rectal pain can be difficult to discuss, but delaying evaluation may prolong symptoms or allow an infection or another treatable condition to worsen. Dr. Aisha Akhtar, a board-certified colon and rectal surgeon, provides respectful, specialized evaluation of hemorrhoids, fissures, abscesses, fistulas, rectal inflammation, prolapse, pelvic-floor symptoms, and other causes of anorectal pain.
Serving Phoenix, Scottsdale, Glendale, and surrounding Arizona communities.
“The whole office was wonderful. Dr Akhtar was excellent. She was thorough. She explained things extremely well. She answered all my questions. I...The whole office was wonderful. Dr Akhtar was excellent. She was thorough. She explained things extremely well. She answered all my questions. I never felt like she was rushing my exam.”
Jaime Peters
★★★★★
“Dr. Akhtar and the entire team made what could have been a very stressful experience feel comfortable, reassuring, and genuinely cared for from sta...Dr. Akhtar and the entire team made what could have been a very stressful experience feel comfortable, reassuring, and genuinely cared for from start to finish. Dr. Akhtar was professional, compassionate, and took the time to thoroughly explain everything before my procedure, which immediately put me at ease. The procedure itself went smoothly, and I truly felt I was in excellent hands the entire time. The office staff was also kind, organized, and attentive throughout the process. I’m incredibly grateful for the level of care, patience, and professionalism I received. I would absolutely recommend Dr. Akhtar to anyone looking for a skilled doctor who truly cares about their patients and their comfort.”
Michelle Abby
★★★★★
“I cannot express the how thankful I am for Dr. Akhtar. I had been to 4 other colorectal doctors, 3 gastro doctors before seeing Dr. Akhtar. I was c...I cannot express the how thankful I am for Dr. Akhtar. I had been to 4 other colorectal doctors, 3 gastro doctors before seeing Dr. Akhtar. I was crying in her office when she met me the first time. That didn't deter her. Not only that but she located the issue on my first visit. She is kind, caring, thorough and incredibly knowledgeable. She listens, spends time with you and doesn't talk over you. I've needed extra time to discuss my case many times and she has always taken the time that I needed. I've brought to her research I've read, and she always already knows about the publications. The staff are kind and helpful. I dont know what I would have done without finding her. Another health care provider recommended her highly as do I.”
Lorena Zeilman
★★★★★
“Best colorectal surgeon I’ve ever met. Dr. Akhtar is compassionate, gentle, warm, and caring. I came to her in Glendale after having a horrific exp...Best colorectal surgeon I’ve ever met. Dr. Akhtar is compassionate, gentle, warm, and caring. I came to her in Glendale after having a horrific experience with a general surgeon in Flagstaff (where I live). The Flagstaff surgeon caused a hemorrhage that almost cost me my life, and then I developed stenosis after the emergency room surgeon “fixed” the hemorrhage. Dr. Akhtar was kind enough to take me as a patient (most surgeons will not take a patient who has already been operated by another surgeon due to liability). She was very respectful and gentle in the examination, and was even able to fit me in for an outpatient procedure under sedation the very same day (knowing that I drove over 2 hours to see her). I could not be happier with her. She took the time to personally call me the next day to check on my progress. You do not see this type of doctor very often anymore. She is someone who is in it for the patient, and you can tell. I will continue to drive over 4 hours there and back to receive her high quality care and expertise. Cannot recommend her highly enough.”
Brianna Stabler
★★★★★
“Dr. Akhtar is THE BEST provider I have ever seen, period. She is incredibly knowledgeable, informative, and above all so kind. I have not met...Dr. Akhtar is THE BEST provider I have ever seen, period. She is incredibly knowledgeable, informative, and above all so kind. I have not met many people who have as comforting a bedside manner as she does. I was educated properly every step of the way and felt confident doing so because of her caring demeanor. Her PA Moses is also so friendly and upbeat, helping to ease any tension you may be feeling prior to the exam. The energy both Dr. Akhtar and Moses bring was paramount to how excellent my experience was here. Given their specialty, it would be easy to have an uncomfortable experience. However, they go the extra mile to make sure you are comfortable and reassured before anything is done. I cannot recommend this practice enough. Thank you Dr. Akhtar for the genuine concern and care you provided to me! Both my body and my outlook on my health outcomes are better off because of you.”
Sheba Shah
★★★★★Oct 13, 2026
“Dr. Akhtar and her office were excellent to work with . They were fast and efficient. Dr. Akhtar made me feel very comfortable. She’s incredibly kn...Dr. Akhtar and her office were excellent to work with . They were fast and efficient. Dr. Akhtar made me feel very comfortable. She’s incredibly knowledgeable and I felt that I was in good hands. She’s a very smart doctor and I’m so glad she took care of me.”
Barry Nestlerode
★★★★★Oct 11, 2026
“DR. AKHTAR is always very attentive and compasionate to my needs a patient. Takes plenty of time to discuss my issues and overall genuine concern....DR. AKHTAR is always very attentive and compasionate to my needs a patient. Takes plenty of time to discuss my issues and overall genuine concern. She is a great person and provider, makes you feel that you are important, not just a number.”
Teeba Alkaissy
★★★★★Oct 6, 2026
“Very caring and attentive doctor. She truly cares about her patients and takes her time explaining everything. 🤍”
Melany Berger
★★★★★Oct 1, 2026
“It is my absolute pleasure to write a review for Dr. Akhtar. After having some tough experiences with doctors along the way, Dr Akhtar is a breath...It is my absolute pleasure to write a review for Dr. Akhtar. After having some tough experiences with doctors along the way, Dr Akhtar is a breath of fresh air and just a lovely person. She made a very uncomfortable situation much easier. Her bedside manner is wonderful. She is detail oriented and actually listened to every, single word I said. She truly cares and wanted me to feel one hundred percent. I trust and feel comfortable with her and haven’t been able to say that about a doctor in a long time. She is skilled, up to date on the latest medical advancements and explains everything in detail as well as takes the time and answers every question. I am so grateful I found her. All of her office staff is so helpful and friendly as well. Thank you for helping me feel like myself again and taking such good care of me. I’ll see you soon. Highly recommend.”
Deb Benhart
★★★★★Oct 1, 2026
“What a great experience with Dr. Ahktar! She was so thorough and knowledgeable explaining everything regarding my sigmoid colectomy! She made me co...What a great experience with Dr. Ahktar! She was so thorough and knowledgeable explaining everything regarding my sigmoid colectomy! She made me comfortable to proceed with the process even after having hesitation! She has an amazing bedside manner and you can tell she truly cares about her patience and their experience! Her office staff is very kind and helpful as well!”